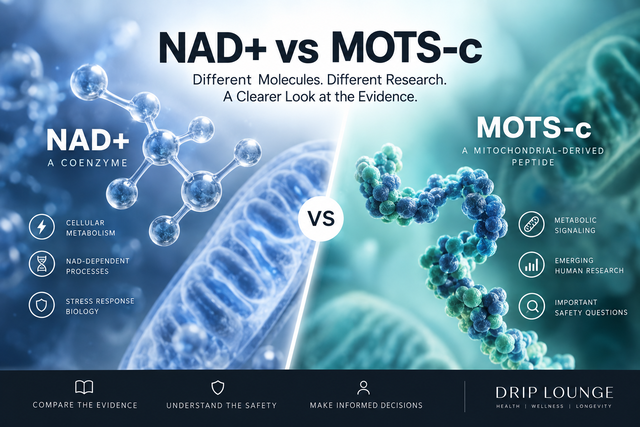
NAD+ and MOTS-c often appear in the same online conversations about mitochondria, metabolism, energy, longevity, and “cellular health.”
That can make them sound like competing versions of the same treatment.
They are not.
NAD+ is a coenzyme involved in normal cellular metabolism and other enzyme-dependent processes. MOTS-c is a mitochondrial-derived peptide being studied for its role in metabolic signaling and stress-response biology.
Their research histories, human evidence, regulatory status, and safety questions are different.
And neither should be selected from an online comparison as a self-directed treatment for fatigue, brain fog, weight concerns, insulin resistance, exercise performance, aging, or another symptom.
Human research involving NAD-related compounds is broader, particularly for oral precursors such as NMN and NR, but evidence varies substantially depending on the compound and administration route. A 2026 systematic review found that oral NAD+ precursors can alter NAD-related biomarkers, while clinical effects across metabolic, vascular, and other outcomes remain inconsistent. The review found no eligible clinical-outcome trials of IV or intramuscular NAD+ itself for anti-aging or wellness indications.
Research involving administered MOTS-c is earlier. A human Phase 2a trial is now recruiting, but results are not yet available.
Written by: Drip Lounge Editorial Team
Medically reviewed by: Megan Nickerson, DNP · Last medically reviewed: September 2026
Regulatory status reviewed: September 18, 2026
Important medical and regulatory information: NAD+ and MOTS-c should not be used to self-treat unexplained symptoms. MOTS-c is not an FDA-approved drug, and FDA materials state that neither MOTS-c free base nor MOTS-c acetate is a component of an FDA-approved drug. Injectable and IV products may also involve separate sourcing, sterility, compounding, and quality considerations.
What Is the Difference Between NAD+ and MOTS-c?
The simplest answer is:
NAD+ is a coenzyme. MOTS-c is a peptide.
NAD+, or nicotinamide adenine dinucleotide, is present throughout the body and participates in cellular redox reactions, energy metabolism, and NAD-dependent enzyme systems.
MOTS-c—short for mitochondrial open reading frame of the 12S rRNA-c—is a small peptide encoded within mitochondrial DNA.
They may both appear in conversations about mitochondrial biology, but being associated with mitochondria does not make them interchangeable.
| Question | NAD+ | MOTS-c |
|---|---|---|
| What is it? | A naturally occurring coenzyme | A mitochondrial-derived peptide |
| Is it a peptide? | No | Yes |
| Main research context | Cellular metabolism, redox biology, NAD-dependent enzymes | Mitochondrial signaling and metabolic adaptation |
| Human research | Considerable research on some oral precursors; much less for injectable/IV NAD+ | Limited; human interventional research is emerging |
| FDA-approved for common wellness claims? | No | No |
| FDA-approved for fatigue or weight loss? | No | No |
| Can the evidence be treated as interchangeable? | No | No |
| Should they be selected based on online claims? | No | No |
This is an educational comparison. It does not establish that either intervention is safe, effective, legally available, or appropriate for an individual.
If you want a deeper introduction to NAD+, start with What Is NAD+ IV Therapy?.
For MOTS-c specifically, see What Is MOTS-c Peptide?.
What Is NAD+?
NAD+ stands for nicotinamide adenine dinucleotide.
It is a coenzyme, meaning it helps enzymes perform chemical reactions.
Among other functions, NAD+ participates in oxidation-reduction reactions central to cellular metabolism and is involved in enzyme systems connected to cellular stress responses and DNA-damage biology.
That biological importance is one reason NAD+ has become popular in wellness marketing.
But an important distinction is often lost:
A molecule being essential to normal biology does not mean administering more of that molecule produces a particular clinical benefit.
For example, NAD+ is involved in energy metabolism.
That does not establish NAD+ injections or IV therapy as proven treatments for fatigue.
NAD+ biology is relevant to metabolic processes.
That does not mean NAD+ IV has been proven to cause weight loss.
If you're interested in that distinction specifically, read Can NAD+ Help With Weight Loss?.
What Does Human NAD+ Research Actually Show?
This is where the specific product matters.
Much of the stronger human research involves NAD+ precursors, particularly oral nicotinamide riboside and nicotinamide mononucleotide, rather than NAD+ itself administered intravenously.
A 2026 systematic review evaluated 113 eligible studies, including 33 human intervention studies.
Oral NR and NMN consistently affected NAD-related biomarkers, but effects on functional, metabolic, vascular, and broader health outcomes were heterogeneous and often absent or limited to particular endpoints.
Importantly, the review found no eligible clinical-outcome trials of intravenous or intramuscular NAD+ itself for anti-aging or wellness outcomes.
A separate September 2026 review reached a similar conclusion about IV NAD+: available evidence remains sparse, generally involving small studies, observational data, uncontrolled investigations, and short follow-up periods. The authors concluded that evidence is currently insufficient to establish routine clinical effectiveness or long-term safety.
This means we should not combine:
NR evidence → NMN evidence → NAD+ injection evidence → NAD+ IV evidence
as though they describe one treatment.
They do not.
What Is MOTS-c?
MOTS-c is a mitochondrial-derived peptide encoded within mitochondrial DNA.
Researchers first described it prominently in 2015. In early experimental work, MOTS-c was studied in cells and mice in relation to metabolic signaling, skeletal muscle, AMPK pathways, insulin sensitivity, and diet-associated metabolic changes.
These experiments helped establish MOTS-c as an interesting research molecule.
But the original findings were largely preclinical.
A mouse showing a metabolic response after experimental MOTS-c administration does not establish that administered MOTS-c is safe or effective for obesity, insulin resistance, fatigue, exercise performance, or longevity in humans.
That distinction is especially important because marketing language often removes the phrase:
“in mice.”
What Does Human MOTS-c Research Show?
Human research exists, but much of it has historically focused on naturally occurring circulating MOTS-c levels, associations with metabolic states, genetic variation, or laboratory research involving human-derived cells.
That is not the same as giving MOTS-c to patients and demonstrating a treatment effect.
A 2024 systematic review and meta-analysis examined relationships between mitochondrial-derived peptides and metabolic states. That type of evidence can identify associations, but observational associations cannot establish that administering MOTS-c will improve the condition being observed.
Even newer laboratory research continues to illustrate this distinction. A 2026 study examined MOTS-c exposure in human mesenchymal stromal cells from people with obesity—but this was an in-vitro cell study, not a clinical treatment trial demonstrating improved patient outcomes.
Is MOTS-c Being Studied in Human Clinical Trials?
Yes—and this is an important update.
A Phase 2a randomized, double-blind, placebo-controlled trial registered on ClinicalTrials.gov began in 2026.
The trial plans to enroll approximately 120 adults with prediabetes and overweight or obesity and evaluate investigational MOTS-c against placebo over a 12-week treatment period.
Its primary outcomes include insulin-sensitivity measurements and treatment-emergent adverse events.
However:
The trial is still recruiting, its estimated completion is in the future, and no study results have been posted.
Therefore, this trial is evidence that MOTS-c is being studied—not evidence that MOTS-c has been shown to work.
That difference is fundamental.
Clinical trial registration ≠ positive trial result ≠ FDA approval ≠ routine medical treatment.
Why Are NAD+ and MOTS-c Often Confused?
Mostly because the marketing language surrounding them overlaps.
Both may be described online using phrases such as:
“mitochondrial support,” “cellular energy,” “metabolic optimization,” “longevity,” “recovery,” “anti-aging,” or “performance.”
Those phrases can create the impression that the two compounds have similar evidence or produce interchangeable outcomes.
They do not.
Consider several common assumptions:
| Common Claim | More Accurate Interpretation |
|---|---|
| “NAD+ and MOTS-c are both mitochondrial treatments.” | They are different molecules studied in different areas of mitochondrial and metabolic biology. |
| “They're both peptides.” | NAD+ is a coenzyme; MOTS-c is a peptide. |
| “Both improve energy.” | Neither should be described as a proven treatment for persistent fatigue. |
| “MOTS-c improves metabolism because animal studies show it.” | Preclinical findings do not establish a human treatment effect. |
| “NAD+ repairs DNA, so it reverses aging.” | Biological participation in enzyme pathways does not prove an anti-aging clinical outcome. |
| “They work differently, so they can be stacked.” | Different mechanisms do not establish combination safety or efficacy. |
| “If it's compounded, it must be approved.” | Compounding and FDA approval are different regulatory concepts. |
For a broader introduction to peptide terminology and clinical caution, see What Is Peptide Therapy? A Beginner's Guide.
NAD+ vs MOTS-c: Which Has More Evidence?
This question is more useful than asking which one is “better.”
NAD+ has a much broader foundational biology literature and considerably more human research involving NAD-related compounds.
But that research is highly fragmented by:
- compound;
- administration route;
- population;
- study design;
- and clinical outcome.
Human research involving oral NMN or NR cannot automatically establish the effectiveness of IV NAD+.
MOTS-c has substantial laboratory and animal research but less human interventional evidence.
The new Phase 2a trial is important because it may begin filling that gap—but until results become available, it cannot answer questions about effectiveness or longer-term safety.
So the current evidence picture is better described as:
| Evidence Type | NAD+ / Related Compounds | MOTS-c |
|---|---|---|
| Foundational biology | Extensive | Established research field, but smaller |
| Cell research | Extensive | Extensive relative to human evidence |
| Animal research | Extensive | Substantial |
| Human observational research | Yes | Yes |
| Human interventional research | More available for oral NR/NMN | Emerging |
| Large trials proving broad wellness claims | No | No |
| Strong long-term parenteral safety data | Limited | Limited |
| FDA-approved treatment for fatigue/weight loss/longevity | No | No |
“More research” should never be translated automatically into “proven treatment.”
Is MOTS-c FDA-Approved?
No FDA-approved MOTS-c drug is currently established.
FDA's July 2026 materials state that neither MOTS-c free base nor MOTS-c acetate has an applicable USP or National Formulary drug-substance monograph and that neither is a component of an FDA-approved drug.
MOTS-c was reviewed during the FDA Pharmacy Compounding Advisory Committee meeting in July 2026 in connection with possible inclusion on the 503A Bulks List.
This requires careful interpretation.
An FDA advisory committee provides non-binding advice to the agency. A committee discussion or favorable recommendation does not itself create FDA approval or automatically place a substance on the 503A Bulks List.
FDA staff's July briefing documents actually proposed that MOTS-c free base and MOTS-c acetate not be included on the 503A Bulks List.
Any subsequent advisory recommendation is still separate from final FDA rulemaking.
This is why phrases such as:
“MOTS-c was approved by the FDA committee”
would be misleading.
FDA approval, advisory committee recommendations, investigational research, and compounding status are four different concepts.
What Does Compounding Status Mean?
Compounded drugs do not become FDA-approved simply because a pharmacy prepares them.
Under section 503A, FDA explains that use of a bulk drug substance depends on specific statutory conditions, including whether a USP/NF monograph exists, whether the substance is a component of an FDA-approved drug, or whether it appears on the applicable 503A Bulks List.
Therefore:
- Scientific interest ≠ FDA approval
- FDA advisory committee review ≠ final FDA action
- Compounding ≠ FDA approval
- Availability online ≠ lawful or clinically appropriate use
These distinctions matter especially with rapidly changing peptide markets.
The regulatory status of MOTS-c should be checked again immediately before this article is published and during every scheduled medical/legal review.
What Safety Questions Exist for MOTS-c?
One of the central problems is that human safety information remains limited.
FDA has specifically listed MOTS-c among bulk substances that may present significant safety risks in compounding, noting potential concerns involving immunogenicity, peptide-related impurities, and active pharmaceutical ingredient characterization.
FDA also stated that it lacked important information needed to determine the safety of MOTS-c administered to humans.
During its July 2026 review, FDA reported that it had not identified publicly available clinical pharmacokinetic studies for MOTS-c-related bulk drug substances.
The newly registered Phase 2a trial may eventually add useful human safety data, but no results are available yet.
That means absence of a long adverse-event list should not be interpreted as evidence that MOTS-c is safe.
Sometimes there simply is not enough human exposure data to characterize the risks well.